


ROI Calculator
See the impact of Dossier with our ROI calculator


ROI Calculator
See the impact of Dossier with our ROI calculator
A wound care nurse is a registered nurse who specializes in preventing, assessing, and treating complex wounds, from pressure injuries and surgical incisions to diabetic ulcers and burns. These nurses combine sharp clinical judgment with hands-on technical skill, and their work directly affects healing times, infection rates, and patient comfort. As the population ages and chronic conditions rise, demand for this specialty continues to grow.
Day to day, a wound care nurse assesses wounds and stages their severity, develops and adjusts treatment plans, and performs procedures such as debridement, dressing changes, and negative pressure therapy. They educate patients and families on care at home, coordinate with physicians and physical therapists, and document progress meticulously. Just as important, they work to prevent wounds in the first place through repositioning protocols, skin assessments, and staff education.
Success in this role rests on a blend of technical and interpersonal competencies. Nurses need advanced wound assessment and staging skills, mastery of dressing and debridement techniques, and a solid grasp of infection control. Because wound care spans many conditions, strong critical thinking is essential for adapting plans as healing progresses. Communication and patient education round out the profile, since much of the healing happens at home under the patient’s own care. Validating these competencies regularly is what keeps a wound care team safe and effective.
The path begins with becoming a registered nurse through an accredited program and passing the NCLEX-RN. From there, nurses typically gain bedside experience, then pursue specialized wound care education and certification, such as the WOCN or WCC credentials. Certification signals verified expertise and often opens doors to higher pay and leadership roles. Many employers support this journey with continuing education and structured competency programs.
How long does it take to become a wound care nurse? After becoming an RN, most nurses gain a year or more of experience before pursuing wound care certification, so the full path typically spans three to five years.
Do you need certification to work in wound care? Not always to start, but certification such as WOCN or WCC is strongly preferred by employers and often required for advanced or lead roles.
Where do wound care nurses work? They practice across hospitals, long-term care, home health, outpatient wound clinics, and rehabilitation settings, wherever complex or chronic wounds need specialized management.
For healthcare organizations, keeping wound care skills current is easier with a competency management platform that keeps skills validated. Explore more on the Dossier blog.
Nurse turnover is expensive, disruptive, and increasingly avoidable. Replacing a single bedside nurse can cost tens of thousands of dollars once recruitment, orientation, and lost productivity are counted, and every departure adds strain to the nurses who remain. The good news is that retention responds to deliberate effort. The strategies below focus on the factors nurses say matter most: respect, growth, support, and a manageable workload.
The first year predicts the rest. A structured onboarding program with clear milestones, preceptor support, and gradual autonomy helps new nurses build confidence instead of burning out. Organizations that treat onboarding as a strategy rather than a formality see dramatically lower first-year turnover.
Nurses stay where they can grow. A clinical ladder or defined advancement path gives them a reason to invest in your organization for the long term, recognizing skill and experience with meaningful progression rather than a vague promise.
Confidence comes from competence. When nurses know their skills are current and validated, they feel safer and more satisfied. Ongoing competency management closes gaps early and signals that the organization is invested in doing the work well.
Recognition does not have to be expensive, but it must be genuine and specific. Timely acknowledgment of good work, peer recognition programs, and fair compensation all tell nurses their contributions are seen and valued.
Chronic understaffing is a leading driver of burnout and departure. Safe staffing ratios, reliable break coverage, and support staff for non-clinical tasks protect nurses from the exhaustion that pushes them out the door.
Nurses often leave managers, not jobs. Investing in nurse leaders who listen, advocate, and coach creates the day-to-day environment that makes people want to stay.
Self-scheduling, predictable shifts, and options like part-time or flexible arrangements help nurses balance work with the rest of their lives, which strongly influences whether they stay.
Address incivility and lateral violence head-on. A respectful, psychologically safe culture is one of the strongest predictors of whether nurses choose to build their careers with you.
Stay interviews and regular pulse surveys only help if leaders visibly act on what they hear. Closing the loop shows nurses their voice shapes the workplace, which builds the trust that underpins retention.
What is the biggest driver of nurse turnover? Burnout from unmanageable workloads and lack of support tops most surveys, closely followed by limited growth opportunities and poor management.
How quickly can retention strategies show results? Some efforts, like recognition and scheduling flexibility, can lift morale within weeks, while structural investments in onboarding and career pathways pay off over the first year and beyond.
Do competency programs really affect retention? Yes. Nurses who feel confident and well-supported in their skills report higher satisfaction and are less likely to leave, especially in their vulnerable early years.
Retention is a system, not a single fix. Dossier helps healthcare organizations strengthen that system through competency management, structured onboarding support, and clear career growth through a clinical ladder.
Lateral violence in nursing refers to hostile, aggressive, or undermining behavior directed by nurses toward their peers. Often described as “nurses eating their young,” it includes everything from overt bullying to subtle sabotage, and it quietly erodes teamwork, morale, and patient safety. Understanding what lateral violence looks like is the first step toward building a healthier, more supportive culture that keeps nurses at the bedside.
Lateral violence, sometimes called horizontal violence or workplace incivility, describes repeated harmful behavior between colleagues at the same level of the hierarchy. Unlike a single bad day, it is a pattern. It can be spoken, such as belittling comments and gossip, or unspoken, such as withholding information, excluding a coworker, or refusing to help. Because much of it happens quietly, it often goes unreported even as it damages the people and teams involved.
Lateral violence shows up in recognizable ways. A nurse may be publicly criticized in front of patients or peers. A new graduate might be set up to fail by being denied guidance during a difficult shift. Eye-rolling, sarcasm, and dismissive body language send a message just as clearly as words. Cliques may exclude certain colleagues from communication, and some staff quietly refuse to assist when a teammate is overwhelmed. Each instance seems small, but together they create a hostile environment.
The consequences reach well beyond hurt feelings. Nurses who experience lateral violence report higher burnout, lower job satisfaction, and a stronger intent to leave, which drives up turnover and its considerable costs. New nurses are especially vulnerable, and a hostile welcome is one of the fastest ways to lose them in their first year. Patient safety suffers too, because nurses who feel unsupported are less likely to speak up, ask questions, or flag concerns. Addressing lateral violence is therefore a retention strategy and a safety strategy at once.
Prevention starts with naming the behavior and setting a clear expectation of zero tolerance, backed by leadership that models respect. Structured onboarding and mentorship give new nurses a safe landing and a trusted person to turn to. Training in communication and conflict resolution equips staff to address tension directly rather than letting it fester. Just as important, organizations should track the competencies and confidence of their teams so that skill gaps, a common trigger for frustration, are closed with support rather than shaming. A strong professional development program signals that the organization invests in its people, which is the foundation of a respectful culture.
Is lateral violence the same as bullying? They overlap. Bullying usually implies a power imbalance, while lateral violence occurs between peers, but both involve repeated harmful behavior that damages individuals and teams.
Who is most affected by lateral violence? New graduates and nurses in their first year are especially vulnerable, though it can affect anyone, and it contributes significantly to early turnover.
What should I do if I witness it? Document what you observe, support the affected colleague, and report the behavior through your organization’s channels so that leaders can address the pattern rather than a single incident.
Building a respectful culture takes more than a policy. See how Dossier helps teams grow confidence through competency management. Strong onboarding and mentorship for new nurses are especially powerful, and you can explore related resources on the Dossier blog.
A patient engagement platform is a software system that helps healthcare organizations communicate with, educate, and involve patients across the entire care journey. Rather than treating patients as passive recipients of care, these platforms give them tools to schedule appointments, access records, message their care team, and follow personalized care plans. The result is a more connected experience that improves outcomes, satisfaction, and operational efficiency at the same time.
At its core, a patient engagement platform connects the systems patients and staff already rely on, such as the electronic health record, scheduling tools, and billing. It then layers on communication channels like secure messaging, text reminders, and patient portals so that information flows in both directions. Automated workflows handle routine touchpoints, including appointment confirmations, pre-visit intake forms, and post-discharge check-ins, freeing clinical teams to focus on the moments that genuinely require a human.
The strongest platforms share a common set of capabilities. Secure two-way messaging keeps conversations documented and compliant. Self-service scheduling and automated reminders cut no-show rates. Educational content delivery meets patients where they are with condition-specific resources. Digital intake and forms remove paperwork from the waiting room. Finally, analytics and reporting show which outreach efforts actually move the needle on engagement and adherence.
For patients, the payoff is convenience and clarity: fewer phone calls, faster answers, and a clearer understanding of their own care. For organizations, engaged patients show up more reliably, adhere to treatment plans more consistently, and report higher satisfaction, which increasingly ties to reimbursement. Well-supported staff also matter here. When frontline teams are confident and competent, patient interactions improve, which is why many organizations pair engagement technology with strong workforce development.
Start by mapping the platform to your actual patient journey rather than a generic feature list. Prioritize deep integration with your EHR, strong security and compliance, and an interface simple enough that patients of all ages will actually use it. Ask vendors how they measure success, what onboarding looks like, and how the tool supports your staff, not just your patients. A platform is only as effective as the people using it, so consider how it fits alongside your broader competency and professional development programs.
Is a patient engagement platform the same as a patient portal? Not quite. A portal is one feature, typically for viewing records and messaging, whereas a full platform coordinates communication, scheduling, education, and analytics across the whole care journey.
How do these platforms improve outcomes? By keeping patients informed and on track between visits, they support better adherence to care plans, reduce missed appointments, and catch issues earlier through consistent check-ins.
Do staff need special training to use one? Most modern platforms are designed to be intuitive, but organizations see the best results when they validate staff skills and provide role-specific onboarding so teams can use the tools confidently.
To learn how Dossier supports engaged patients through a confident, well-validated workforce, explore our competency management platform. You can also explore related insights on the Dossier blog.
The first 90 days shape whether a new nurse thrives or walks away. Strong onboarding reduces first-year turnover, shortens time to competence, and protects patient safety while a nurse is still finding their footing. This guide lays out a step-by-step onboarding process and a practical timeline, from pre-boarding through the end of the first three months, so managers and educators can give every new hire a consistent, supportive start.
First-year turnover among new graduate nurses is costly and disruptive, and much of it traces back to onboarding that felt rushed, inconsistent, or unsupported. A structured program does the opposite: it sets clear expectations, pairs the nurse with a trained preceptor, and validates competencies before the nurse takes on a full, independent assignment. The payoff is a more confident nurse, a safer unit, and lower replacement costs.
Onboarding starts before the first shift. Complete paperwork, credential verification, and system access in advance so day one is about people, not forms. Send a welcome message, share the schedule, and assign a preceptor early. Confirm required licenses and certifications are on file. Handling logistics up front lets the new nurse focus on learning the unit rather than chasing badges and passwords.
The first week centers on orientation to the organization and the unit: mission and values, safety and emergency procedures, documentation systems, and a tour of the space. Introduce the new nurse to the team and clarify who to go to for what. Keep patient responsibility light this week so the focus stays on orientation, relationships, and baseline system training.
This is the core of onboarding. Working alongside a trained preceptor, the new nurse gradually takes on patients while core competencies are observed and validated. Build a checklist of unit-specific skills, from high-frequency tasks to high-risk procedures, and sign each off as the nurse demonstrates it. Regular check-ins between preceptor, nurse, and manager keep progress visible and catch struggles early rather than at the point of failure.
As competencies are validated, the nurse takes a fuller assignment while the preceptor steps back into a supporting role. Introduce more complex patients and situations deliberately. Hold formal check-ins around day 30, day 60, and day 90 to review progress against the competency checklist, address gaps, and set goals. By the end of week 12, most new nurses are ready for a full independent assignment with normal support.
Onboarding should not end abruptly at 90 days. Extend support through a nurse residency, cohort meetings, or continued mentoring, especially for new graduates. Keep tracking competencies and identify development goals that feed into the clinical ladder. This bridge from onboarding into ongoing professional development is where first-year retention is won.
Running a consistent onboarding program across many units and cohorts is hard on paper and spreadsheets. A digital platform gives every new nurse an onboarding checklist, lets preceptors sign off skills in real time, and gives managers a live view of who is on track and who needs support. That visibility turns onboarding from a paperwork exercise into a measurable, repeatable process.
How long should new nurse onboarding last? Core onboarding typically runs 8 to 12 weeks, with new graduates often supported for a full year through a residency program.
What is the difference between orientation and onboarding? Orientation is the early introduction to the organization and unit, while onboarding is the longer process of building competence and integrating the nurse into the team.
Who is responsible for onboarding a new nurse? It is shared: the manager owns the program, a trained preceptor guides day-to-day learning, and educators support competency validation.
For teams building a strong start, Dossier supports nurse residency programs and provides ready-to-use nursing competency checklists.
Nursing leadership is not one-size-fits-all. The best nurse leaders shift their approach based on the situation, the team, and the stakes involved. This guide defines the major leadership styles in nursing, explains the strengths and trade-offs of each, and shows when each works best. Whether you are a charge nurse, a new manager, or a nurse building toward a leadership role, understanding these styles helps you lead more intentionally and adapt as circumstances change.
Transformational leaders inspire teams around a shared vision, encourage growth, and model the standards they expect. This style is strongly associated with higher engagement, better retention, and improved patient outcomes, which is why it underpins Magnet-recognized organizations. Use it to build long-term culture, develop staff, and drive sustained improvement. Its limitation is that vision alone does not resolve an urgent crisis, so pair it with more directive approaches when speed matters.
Transactional leadership runs on clear expectations, structure, and rewards or corrections tied to performance. It keeps routine operations predictable and is effective for compliance-heavy tasks such as medication safety and documentation standards. Use it to maintain consistency and accountability. Relied on alone, it can feel rigid and may limit the innovation and morale that transformational approaches encourage.
Democratic leaders invite input and build decisions collaboratively. This style shines in shared governance, practice-change initiatives, and any situation where staff buy-in determines success. Nurses feel ownership, and better ideas surface. The trade-off is time: participative decision-making is slower, so it is a poor fit for emergencies that demand an immediate call.
Laissez-faire leaders take a hands-off approach, giving staff wide autonomy. With a highly experienced, self-directed team, this can empower experts and spark innovation. On units with newer nurses or unclear standards, it risks inconsistency and safety gaps. Use it selectively, and only where competence and accountability are already well established.
Servant leaders put the needs of their team first, removing barriers so nurses can do their best work. This style builds deep trust and psychological safety, supporting wellbeing and retention. It works well alongside transformational leadership. The caution is that prioritizing the team must not slow decisions when patient safety requires firm, timely direction.
The most effective nurse leaders are situational, flexing their style to fit the moment. In a code, directive leadership saves seconds and lives. When rolling out a new protocol, a democratic approach earns buy-in. When developing a promising new nurse, transformational and servant styles accelerate growth. Reading the situation, the team’s readiness, and the urgency, then choosing the right style, is the core skill of nursing leadership.
Developing as a leader starts with self-awareness: identify your default style and the situations where it serves you well or holds you back. Seek feedback, find a mentor, and pursue formal development through certifications or leadership programs. Organizations can accelerate this by mapping leadership competencies and tracking growth over time, giving nurses a clear development path instead of leaving it to guesswork.
What is the best leadership style in nursing? Research most often points to transformational leadership for its links to engagement, retention, and outcomes, but the best leaders adapt their style to the situation.
Why do leadership styles matter in nursing? They directly affect team morale, retention, patient safety, and quality of care, making leadership a clinical issue, not just an administrative one.
Can a nurse use more than one leadership style? Yes. Effective nurse leaders blend styles and shift between them depending on the team and the situation.
To support leaders at every stage, Dossier helps healthcare teams manage nursing competencies and build structured career pathways through clinical laddering.
A clinical ladder program is a structured, multi-level framework that lets nurses advance in their careers by demonstrating growing clinical expertise, leadership, and professional contribution rather than by leaving the bedside for management. Where a traditional promotion path forces nurses to choose between staying in direct patient care and moving up, a clinical ladder program rewards deepening practice at every stage. This guide breaks down how these programs work, walks through the typical levels with real examples, and explains exactly what nurses must show to climb from one rung to the next.
At its core, a clinical ladder program is a career progression system built around defined competencies. Each level, or rung, carries a clear set of expectations spanning clinical skill, evidence-based practice, education, and professional involvement. Nurses apply or are nominated to advance, assemble evidence that they meet the next level’s criteria, and are reviewed by a committee. Most programs tie each rung to recognition such as a pay differential, a title change, or expanded responsibilities. The result is a transparent path that keeps expert clinicians engaged and at the bedside.
Hospitals invest in clinical ladders because they solve several problems at once. They improve retention by giving experienced nurses a reason to stay and grow. They strengthen quality and safety by rewarding evidence-based practice and continuous learning. They also support Magnet recognition and similar designations, which expect a formal professional advancement structure. competency management platform
or nurses, the payoff is recognition, higher earning potential, and a defined route to leadership that does not require abandoning clinical work.
Most clinical ladder programs use four levels, sometimes labeled Clinical Nurse I through IV. Level I is the entry rung for new graduates and nurses still building core competency, focused on safe, independent practice under the unit’s standards. Level II recognizes the proficient nurse who consistently delivers strong care, mentors newer staff informally, and begins engaging in unit initiatives. Level III marks the expert practitioner who leads projects, applies evidence to change practice, and serves on committees. Level IV is reserved for nurses whose influence extends beyond the unit through research, published work, system-wide initiatives, or formal precepting and teaching roles.
Learn how Dossier supports clinical laddering
Consider a medical-surgical nurse named Maria. As a Level I nurse in her first year, she focuses on mastering her unit’s protocols and passing all required competencies. By her third year she reaches Level II, precepting new hires and joining the unit’s falls-reduction group. At Level III she designs and leads a project that lowers catheter-associated infections, presenting the results to nursing leadership. Reaching Level IV, she co-authors a poster for a national conference and helps standardize the protocol across the hospital system. Each rung is documented with concrete evidence, not just tenure.
Advancement almost always rests on a portfolio of evidence rather than a single review. Common requirements include validated clinical competencies, continuing education hours or certifications, participation in committees or shared governance, evidence of mentoring or precepting, and a quality-improvement or evidence-based practice contribution. Higher rungs add expectations around leadership, research, and influence beyond the immediate unit. Because the criteria are competency-based, the program stays fair and repeatable across departments.
Designing a clinical ladder starts with defining the competencies and evidence required at each level, then building a fair application and review process. The operational challenge is managing the documentation: tracking competencies, certifications, and portfolio evidence for hundreds or thousands of nurses. Many organizations move this off spreadsheets and into a competency management platform such as Dossier, where each nurse’s skills, credentials, and advancement evidence live in one auditable record. That visibility makes review committees faster and keeps the program defensible for accreditation.
Is a clinical ladder the same as a career ladder? Not quite. A career ladder can include moves into management or education, while a clinical ladder specifically rewards advancing clinical expertise while staying in direct patient care.
How long does it take to move up a level? It varies by program, but most require a minimum time in the current role plus documented evidence, often one to three years between rungs.
Do clinical ladder programs come with a raise? Usually yes. Most programs attach a pay differential or bonus to each level, though the structure differs by employer.
Are clinical ladders only for hospitals? No. While common in hospitals, similar frameworks exist in long-term care, ambulatory settings, and large health systems.
QSEN competencies are six core areas of knowledge, skills, and attitudes that nurses need to continuously improve the quality and safety of patient care. Developed by the Quality and Safety Education for Nurses (QSEN) project, they are: patient-centered care, teamwork and collaboration, evidence-based practice, quality improvement, safety, and informatics.
QSEN stands for Quality and Safety Education for Nurses. It is a national initiative, launched in 2005 with funding from the Robert Wood Johnson Foundation, created to prepare nurses with the competencies needed to continuously improve the quality and safety of the healthcare systems in which they work. QSEN defines each competency in terms of the knowledge, skills, and attitudes (KSAs) nurses should develop.
QSEN competencies matter because they translate the broad goals of “quality” and “safety” into concrete, teachable, and assessable skills. They give nursing schools a shared framework for curricula, give employers a common language for onboarding and competency validation, and ultimately help reduce preventable harm and improve patient outcomes. For practicing nurses, they provide a clear map of the behaviors that define safe, high-quality care.
The six competencies build on one another to support safe, effective care. Patient-Centered Care means recognizing the patient as the source of control and full partner in care. Teamwork and Collaboration means functioning effectively within nursing and interprofessional teams. Evidence-Based Practice means integrating best current evidence with clinical expertise and patient preferences. Quality Improvement means using data to monitor outcomes and improve care processes. Safety means minimizing risk of harm to patients and providers through both system effectiveness and individual performance. Informatics means using information and technology to communicate, manage knowledge, and support decision-making.
Here is a quick reference to the six competencies and their focus. Patient-Centered Care, the patient as partner and source of control. Teamwork and Collaboration, effective functioning in interprofessional teams. Evidence-Based Practice, integrating evidence, expertise, and patient values. Quality Improvement, using data to improve care processes and outcomes. Safety, reducing risk of harm through systems and individual performance. Informatics, using technology and data to support safe decision-making.
Nursing programs embed QSEN competencies into coursework, simulations, and clinical evaluations, while healthcare organizations use them to structure orientation, annual competency assessments, and professional development. Because each competency is defined through knowledge, skills, and attitudes, they can be observed, taught, and validated, making them a natural backbone for a nurse competency program.
Assessing six competencies across an entire nursing workforce is difficult on paper. Many organizations use a competency-management platform to map QSEN-aligned skills to roles, assign and document validations, track evidence of knowledge, skills, and attitudes over time, and generate reports for accreditation and quality reviews. This makes it possible to demonstrate, not just assert, that staff meet quality and safety standards.
What are the 6 QSEN competencies? They are patient-centered care, teamwork and collaboration, evidence-based practice, quality improvement, safety, and informatics.
When was QSEN created? The QSEN project was launched in 2005 with funding from the Robert Wood Johnson Foundation to build quality and safety competencies into nursing education.
What are KSAs in QSEN? KSAs stand for knowledge, skills, and attitudes. QSEN defines each of the six competencies through specific KSAs that nurses should develop and demonstrate.
Are QSEN competencies only for nursing students? No. While QSEN began in nursing education, the competencies are widely used in practice settings for onboarding, ongoing competency validation, and quality improvement among practicing nurses.
A nursing competency checklist is a structured tool used to verify that a nurse can safely and correctly perform the specific skills required for their role. It lists each competency, the criteria for success, and a place for a preceptor or manager to validate and date the demonstration, turning “trained” into documented, verifiable proof of “competent.”
A nursing competency checklist is a document that breaks a role down into its required skills and behaviors, then provides a standardized way to assess and record whether each one has been demonstrated. Rather than assuming competence from a completed course, the checklist captures observable evidence: the skill, the standard, the method of validation (observation, return demonstration, simulation), and the validator’s signature and date.
Checklists are used during onboarding, annual competency validation, cross-training to new units, and whenever new equipment or procedures are introduced.
Competency checklists protect patients and organizations alike. They ensure every nurse can actually perform critical skills, create a consistent standard across a unit or facility, and produce the documentation that accreditors and regulators require. For managers, they replace guesswork with evidence; for nurses, they clarify exactly what is expected and provide a fair, transparent record of their abilities.
An effective checklist is specific, measurable, and easy to use at the point of validation. Core elements include: the employee and role, the competency or skill name, the performance criteria or standard, the validation method, a rating or pass/fail indicator, the validator’s name and credentials, the date, and space for comments or a remediation plan. Grouping skills by category, such as safety, clinical procedures, documentation, and equipment, keeps long checklists organized.
Below is a simple template structure you can copy into a document or spreadsheet and adapt to any role. For each skill row, capture: Skill / Competency; Standard / Criteria; Validation Method (observation, return demo, simulation, written); Met / Not Met; Validator Name & Credentials; Date; and Comments / Remediation. Add category headers (for example, Infection Control, Medication Administration, Emergency Response) and a signature block at the bottom for the nurse and the validator.
While every role differs, common competencies include hand hygiene and infection control, medication administration and the rights of medication safety, IV insertion and management, wound care, patient assessment and vital signs, use of key equipment (pumps, monitors, lifts), emergency response and code participation, and accurate documentation. Specialty units add role-specific skills such as telemetry interpretation, ventilator management, or chemotherapy administration.
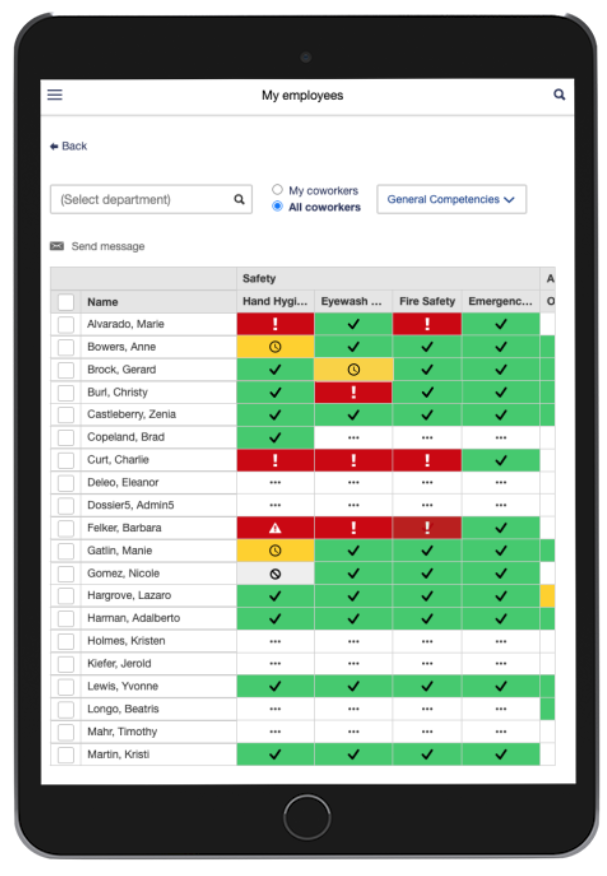
Paper checklists work for one nurse but break down across a large workforce, where skills, certifications, and due dates must be tracked for hundreds of staff. Many organizations move to a competency-management platform that digitizes checklists, routes validations to preceptors, stores evidence centrally, flags expiring competencies and certifications, and generates audit-ready reports on demand. This turns competency validation from a filing-cabinet burden into a real-time view of workforce readiness.
What is the difference between a competency checklist and a skills checklist? The terms are often used interchangeably. Both list required skills and record validation, though “competency” checklists tend to emphasize the standard of performance and evidence of ability, not just whether a task was attempted.
How often should nursing competencies be validated? Typically at hire, at the end of orientation, and at least annually, plus whenever new equipment, procedures, or roles are introduced. Your organization’s policy and accreditation requirements set the exact cadence.
Who validates a nursing competency? A qualified validator, usually a preceptor, charge nurse, educator, or manager with demonstrated competence in that skill, observes and signs off. High-risk skills may require validation by a specialty-certified nurse or educator.
Can competency checklists be digital? Yes. Digital checklists and competency-management platforms make it easier to standardize, route, store, and report validations, and they automatically track expirations, reducing manual tracking and audit risk.
A healthcare LMS (learning management system) is software built to deliver, track, and document training, competencies, and continuing education for clinical and non-clinical staff. To choose the right platform, prioritize regulatory compliance tracking, competency management, clinical content, integrations with your HR and credentialing systems, and reporting that stands up to accreditation audits.
A healthcare LMS is a learning management system designed specifically for the needs of hospitals, health systems, long-term care, and other care settings. Beyond hosting courses, it manages mandatory compliance training, tracks license and certification expirations, documents demonstrated competencies, and produces the audit-ready records required by regulators and accreditors such as The Joint Commission and CMS.
General-purpose corporate LMS platforms can host videos and quizzes, but healthcare LMS platforms add the compliance, competency, and credentialing capabilities that patient-care environments demand.
Healthcare training is higher-stakes and more heavily regulated than most industries. Staff must complete recurring compliance modules, maintain licensure, and prove hands-on competency, not just watch a course. The right platform reduces compliance risk, shortens onboarding, standardizes skills across units, and gives leaders visibility into workforce readiness. The wrong platform creates manual tracking, audit gaps, and frustrated staff.
When evaluating a healthcare LMS, focus on the capabilities that map to real clinical and regulatory needs rather than a long generic feature list. The most important include: compliance and mandatory-training automation, competency management with skills validation, license and certification tracking with expiration alerts, a library of accredited clinical content (or easy content authoring), role- and unit-based assignments, robust audit-ready reporting, and integrations with HRIS, scheduling, and credentialing systems. Mobile access and a clean learner experience also drive completion rates.
This is where healthcare LMS platforms earn their keep. Look for automated assignment of required training by role, automatic reminders before due dates, complete audit trails, and one-click reporting that maps to accreditation standards. The ability to show a surveyor exactly who completed what, and when, can turn a stressful audit into a routine one.
A course completion tells you someone watched training; a competency tells you they can actually perform a skill safely. Strong platforms go beyond “click and complete” to capture skills checklists, preceptor sign-offs, and evidence of demonstrated ability. This distinction matters most for clinical roles, where the goal is verified capability, not just attendance. Organizations focused on true clinical competency often pair or replace a traditional LMS with a dedicated competency-management platform that centralizes skills, certifications, and validation in one auditable system.
Run a structured evaluation rather than relying on a demo alone. Define your must-have requirements, involve nursing education and compliance stakeholders early, and score each vendor against the same criteria. Ask for references from similar organizations, test the reporting with your own audit scenarios, confirm integration support, and clarify total cost including implementation and ongoing content. A short pilot with real users is the best predictor of adoption.
What is the difference between an LMS and a healthcare LMS? A general LMS delivers and tracks training for any industry. A healthcare LMS adds compliance automation, competency management, license and certification tracking, and audit-ready reporting tailored to clinical settings and accreditation requirements.
How much does a healthcare LMS cost? Pricing varies widely based on the number of users, features, and content libraries, and is usually quoted per user per year plus implementation. Always confirm whether accredited clinical content and integrations are included or priced separately.
Does a healthcare LMS handle competency management? Some do to a degree, but competency management, skills validation, preceptor sign-offs, and evidence of demonstrated ability, is often deeper in dedicated competency platforms. Confirm exactly how a vendor captures and reports true competency, not just course completion.
What integrations should a healthcare LMS have? At minimum, look for integrations with your HRIS, scheduling, and credentialing systems so that roles, assignments, and certification data stay in sync automatically and reduce manual data entry.